
Myth #3: Oral Medications Work Better Than Topical Medications
A prescription doesn’t have to travel through the entire body to be effective. In dermatology, sometimes the most direct route is exactly where the treatment needs to be.
 Medically reviewed byKnox Beasley, MD, FAADDermatologist

THE MYTH:
“If it’s a pill, it must be stronger—and if it’s stronger, it must work better.”
THE REALITY:
Not necessarily.
In dermatology, the route a medication takes into the body does not determine how effective it will be. The right treatment depends on the condition being treated, its severity and location, the medication’s mechanism of action, and the individual patient.
In fact, current dermatology treatment guidelines recommend topical medications as important—and sometimes first-line—therapies for several common skin conditions.
So, while swallowing a pill may feel like bringing in the heavy artillery, dermatology is a little more complicated than that.
Let's look at what actually happens when a medication goes on your skin versus into your stomach, and why your dermatologist may intentionally choose one over the other.
Why Do We Assume Pills Are Stronger?
The misconception is understandable.
We're accustomed to taking oral medications for conditions affecting the entire body. When something feels serious, we're often handed a tablet or capsule.
Meanwhile, topical treatments are creams, gels and lotions; the same types of products sitting on the skincare shelf at Target.
It's easy to subconsciously put them into two categories:
Pill = medicine.
Cream = skincare.
Pharmacologically, that distinction doesn't hold up.
Prescription topical medications can contain potent active pharmaceutical ingredients. Topical corticosteroids, retinoids, calcineurin inhibitors and other prescription drugs can produce clinically meaningful effects in the tissue where they're applied.
The real question isn't:
“Which route is stronger?”
It's:
“Where does the medication need to work?”
A Quick Pharmacology Lesson—Without the Med School Tuition
Your skin isn't just wrapping paper for your body.
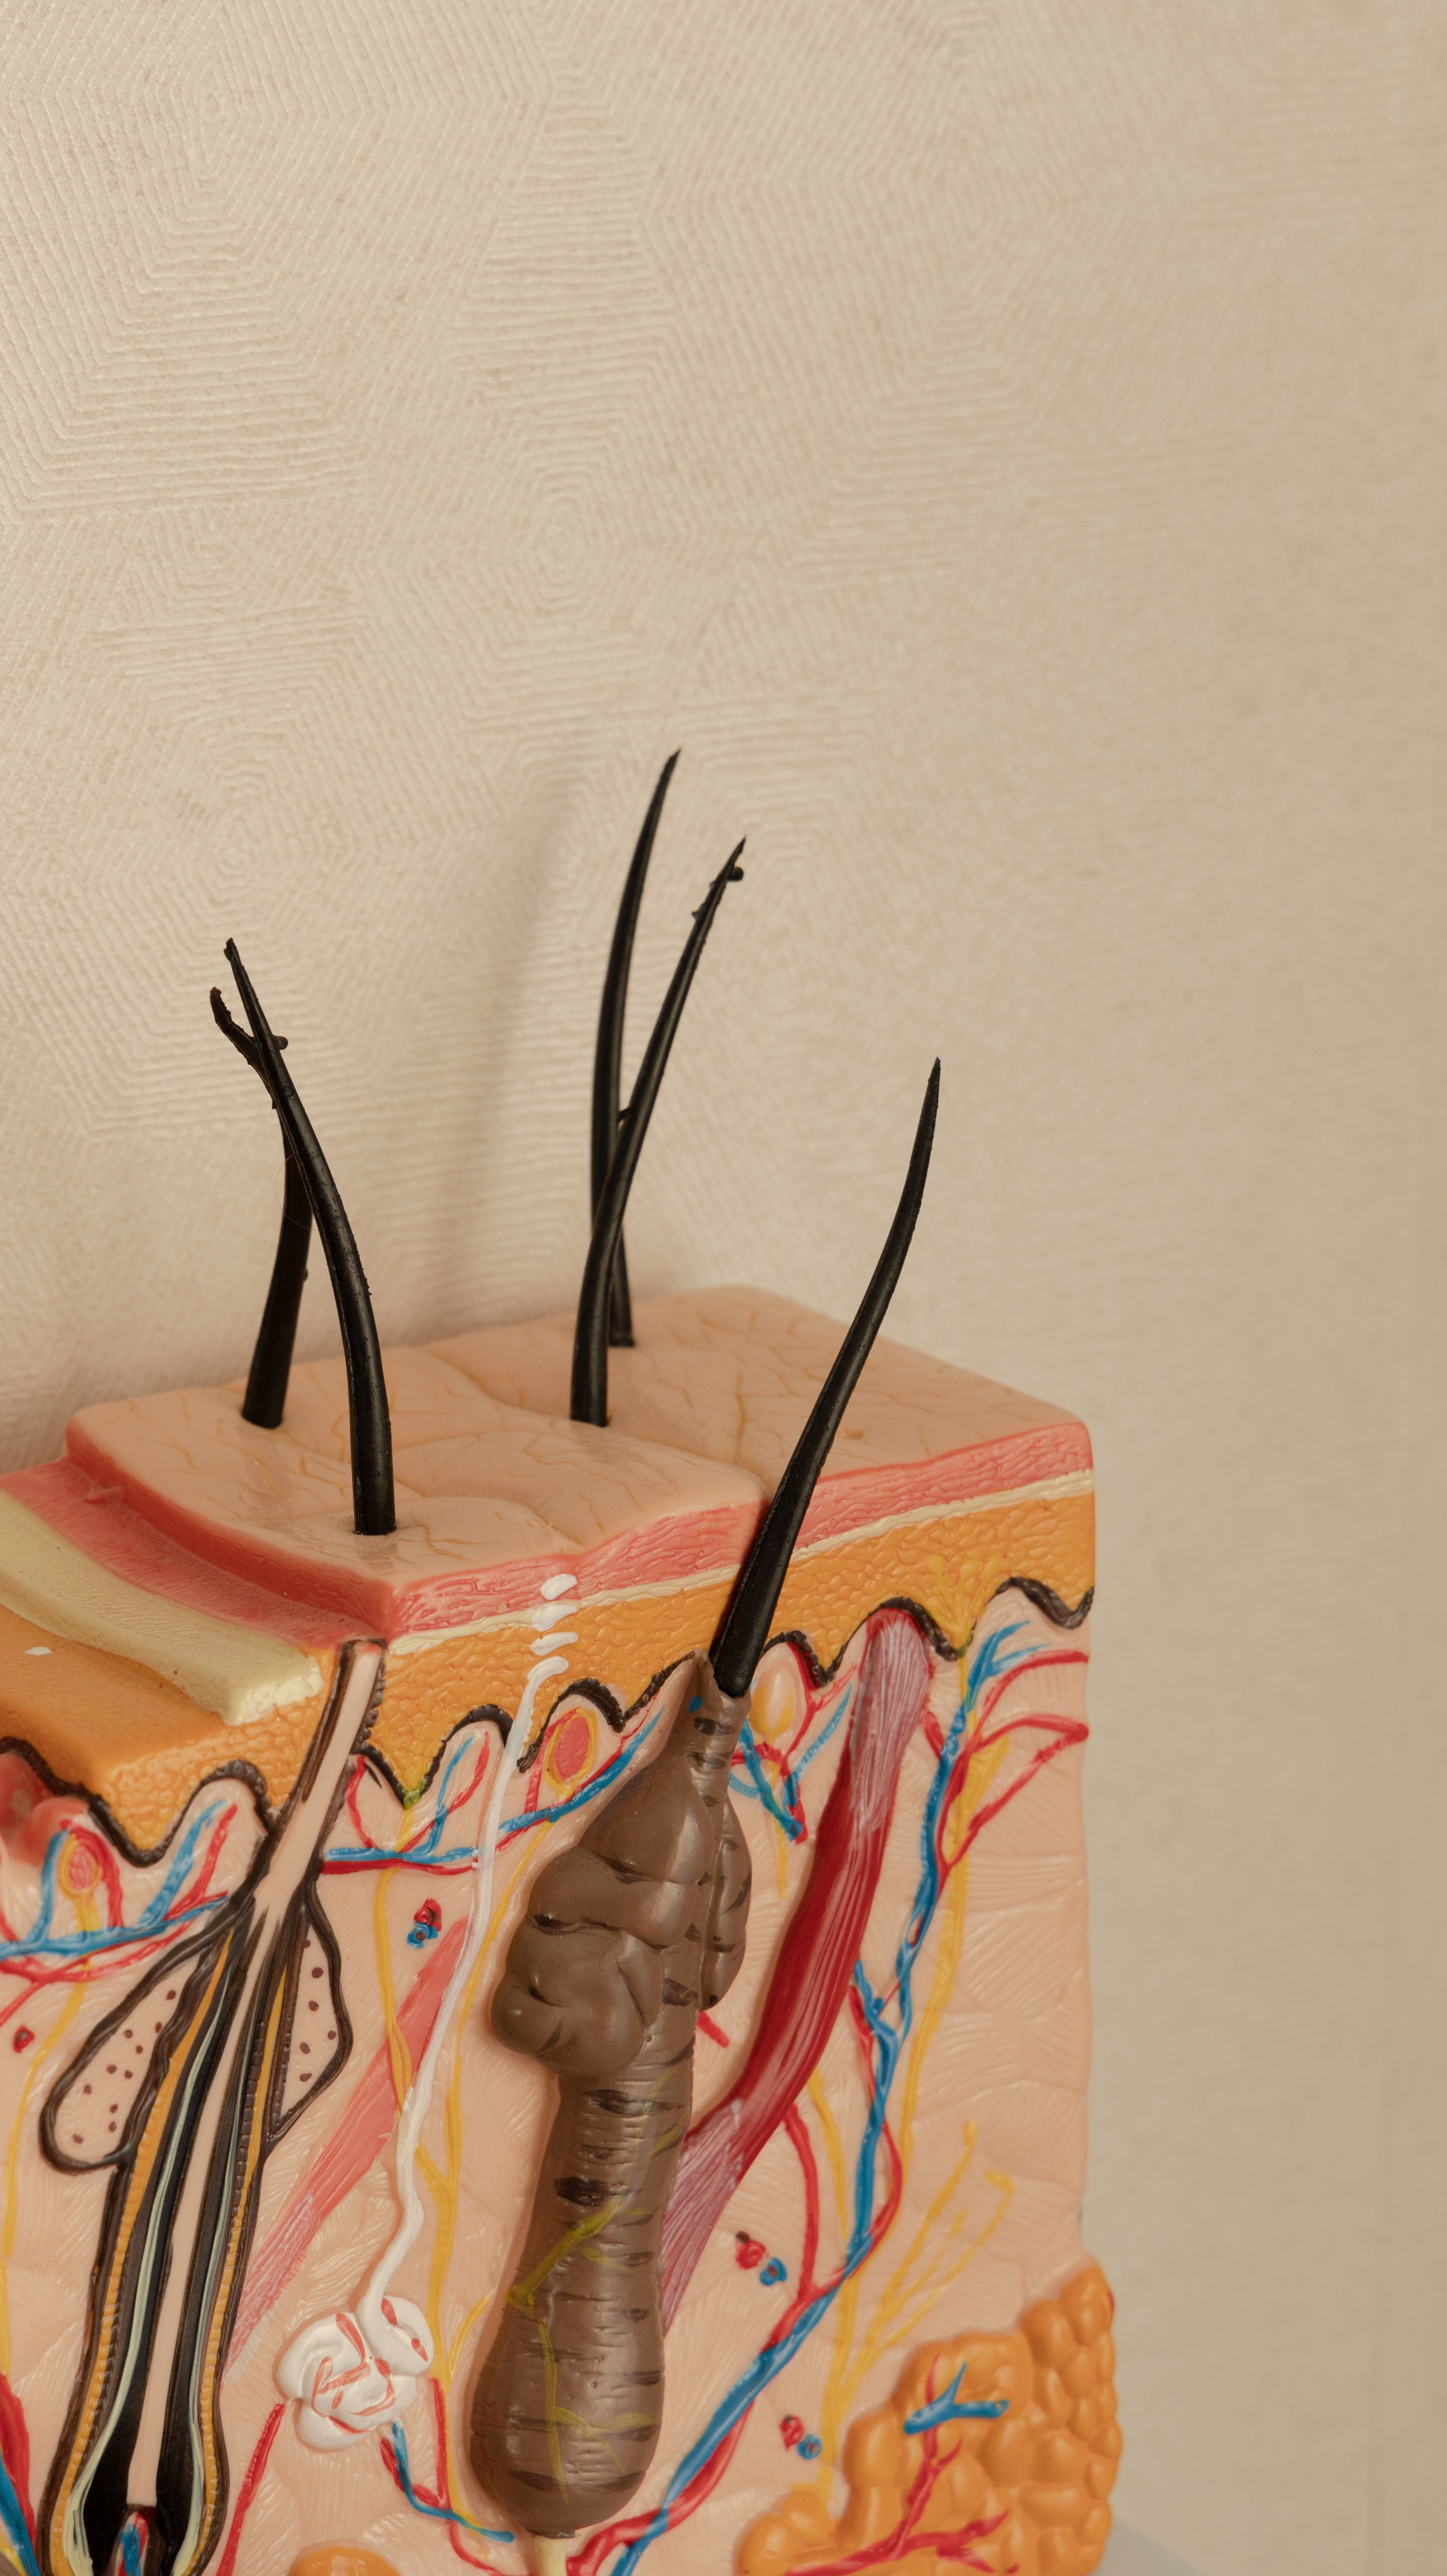
It's an organ with multiple layers, and its outermost layer, the stratum corneum, acts as an important barrier between your body and the outside environment.
For a topical medication to work, its active ingredient generally needs to leave its formulation, interact with or penetrate the skin barrier to the degree required, and reach the appropriate target within the skin.
And this is where formulation science becomes important.
A medication's topical vehicle—whether it's an ointment, cream, lotion, gel, solution or another formulation—isn't simply packaging. Vehicle characteristics can influence drug delivery, application, tolerability and adherence. A peer-reviewed review of topical drug-delivery vehicles notes that vehicles facilitate delivery across the stratum corneum into deeper skin regions while generally minimizing systemic absorption.
In other words:
The cream isn't just carrying the medicine. The choice of vehicle can influence how the medication is delivered to the skin, how it spreads and absorbs, and how well a patient tolerates using it.
That doesn't mean every topical penetrates equally, nor does it mean topical therapy always avoids systemic absorption. The active ingredient, concentration, vehicle, application area, skin integrity and other factors all matter.
But it does help explain why “it's only topical” isn't a particularly useful way to judge a medication.
What Do Actual Dermatology Guidelines Say?
This is where the myth really starts to fall apart.
Instead of judging a treatment by how it’s taken, let’s look at where topical and oral medications actually fit into current dermatology guidelines.
Acne: Topicals Are Foundational Treatments
The 2024 American Academy of Dermatology acne guideline, published in the Journal of the American Academy of Dermatology, was developed using a systematic review and the GRADE framework for evaluating evidence.
The guideline issued strong recommendations for benzoyl peroxide, topical retinoids and topical antibiotics, alongside a strong recommendation for oral doxycycline. Other therapies received conditional recommendations based on the evidence and clinical circumstances.
That's an important distinction.
The guideline doesn't establish a ladder where “cream” sits at the bottom and “pill” automatically sits at the top. Instead, topical and systemic medications each have specific roles.
AAD guidance also emphasizes combining treatments with different mechanisms of action and recommends limiting systemic antibiotic use when possible.
So for acne, reaching for an oral medication first isn't automatically a more aggressive or more evidence-based choice.
Sometimes the topical is exactly where the evidence points.
Atopic Dermatitis: Strong Recommendations for Topical Therapy
We see a similar pattern with eczema, or atopic dermatitis.
The AAD's updated guidelines for adults made strong recommendations for several topical therapies for atopic dermatitis, including topical corticosteroids, topical calcineurin inhibitors, topical PDE-4 inhibitors and topical JAK inhibitors.
Systemic treatments absolutely have a role in appropriate patients with more significant disease.
But again, oral or systemic administration isn't automatically the superior route simply because medication circulates throughout the body.
Psoriasis: Disease Severity Helps Determine the Route
Psoriasis gives us another good example.
Joint AAD-NPF psoriasis guidelines note that many patients with mild-to-moderate psoriasis can be successfully treated with topical agents. Topical corticosteroids are recommended for plaque psoriasis outside intertriginous areas, and steroid-sparing topical agents can be used alone or in combination depending on the situation.
For moderate-to-severe disease, systemic medications and biologics may become appropriate.
Topicals don't necessarily disappear at that point, either. AAD guidance notes that topical treatments may be combined with systemic or biologic therapies.
That's a recurring theme in dermatology:
Topical and oral medications aren't necessarily competitors. They're tools that often work together.
MYTH: “Topicals Don't Get Deep Enough to Actually Work.”
This one sounds scientific—but it's overly simplistic.
The skin barrier certainly limits penetration. That's one of its jobs.
But topical medications and their vehicles are developed specifically with skin delivery in mind. Drug properties and formulation can affect how an active ingredient moves into or through the stratum corneum and reaches its intended target.
And not every dermatologic drug needs to reach the bloodstream to accomplish its therapeutic goal.
For many skin diseases, the target is in the skin.
That's an important difference between topical treatment and transdermal treatment. A topical dermatologic medication generally aims to produce an effect at or within the skin, whereas transdermal delivery is designed to move medication through the skin and into systemic circulation.
So “it doesn't get into your bloodstream very much” isn't necessarily evidence that a topical medication failed.
In some cases, that's part of the point.
MYTH: “If One Ingredient Works, Three Must Work Three Times Better.”
Not quite. Pharmacology unfortunately refuses to be that convenient.
Combination therapy can be valuable when individual medications address different components of a disease—but adding ingredients indiscriminately does not guarantee better outcomes and may increase complexity, irritation or other adverse effects.
Acne provides a good example of rational combination therapy.
The AAD recommends using topical therapies with different mechanisms of action as a good clinical practice approach.
Psoriasis offers another example: AAD guidance describes the use of steroid-sparing agents alone or in combination with corticosteroids, and AAD patient guidance notes evidence that combining a vitamin D analogue with a corticosteroid can be more effective than either used alone in appropriate circumstances.
The key word is rational combination therapy.
More ingredients ≠ automatically better treatment.
The goal is to choose medications that make sense together for the diagnosis and patient.
So Where Does Compounding Fit?
This is where topical therapy gets especially interesting.
Commercially manufactured medications are produced in predetermined formulations. The active ingredient, strength, vehicle, and inactive ingredients have already been selected by the manufacturer. For many patients, those available options may fit their treatment needs well.
But dermatology is rarely one-size-fits-all.
Compounded medications give the prescriber flexibility to design a formulation around an individual patient's needs. Rather than being limited to commercially manufactured combinations, strengths, and dosage forms, a prescriber can determine which appropriate ingredients are included, select their strengths, choose the vehicle, and, when clinically appropriate, leave out certain ingredients.
What Can Be Customized?
Depending on the medication and clinical situation, a compounded topical prescription may allow a prescriber to consider:
Active ingredients: More than one compatible medication may sometimes be incorporated into a single formulation when clinically appropriate.
Strengths: The prescribed concentration of an ingredient may be individualized when an appropriate patient-specific need exists.
Vehicle: A prescriber may select a cream, gel, ointment, solution, lotion, foam, or another suitable dosage form based on factors such as the treatment area, medication properties, and patient needs.
Certain ingredients: A formulation may sometimes be prepared without a particular inactive ingredient when there is a clinically appropriate reason to avoid it.
The overall formulation: Rather than viewing the active drug and its vehicle as completely separate decisions, the prescriber can consider how the entire formulation fits into the patient's treatment plan.
This becomes particularly relevant when a dermatologist wants to address more than one aspect of a condition.
For example, combination therapy is already an established concept in dermatology. Current acne guidelines recommend combining therapies with different mechanisms of action when appropriate. Compounding can provide one way, in suitable patients, to place compatible prescribed ingredients into a single topical formulation.
That does not mean adding more ingredients automatically creates a better medication. Each ingredient still needs a clinical reason for being there, and the combination must be appropriate for the patient.
Instead, the benefit is flexibility.
The prescriber isn't necessarily limited to asking, "Which manufactured product is closest to what I want?" In appropriate circumstances, compounding can allow the prescription to be built around specific patient needs.
And that brings us right back to the myth at the center of this article.
A topical medication should not be dismissed as "just a cream." The active ingredient matters. The strength matters. The vehicle matters. The combination of ingredients can matter. Most importantly, the clinical reasoning behind the prescription matters.
When Oral Medication Does Make More Sense
There are absolutely situations in dermatology where systemic treatment may be preferred or necessary.
Disease severity, extent, location, response to previous therapy, associated symptoms, comorbidities, and effects on quality of life can all influence treatment selection.
Acne is a good example. Topical medications play an important role in acne treatment, but oral antibiotics such as doxycycline may also be appropriate for some patients, particularly when treating moderate-to-severe inflammatory acne. Current American Academy of Dermatology (AAD) guidelines include recommendations for both topical and systemic therapies, emphasizing that treatment selection should reflect the patient's individual clinical needs.
But severity isn't the only reason a dermatologist may consider moving from a topical medication to an oral one.
Sometimes the Treatment Just Isn't Working
A topical treatment may be an appropriate place to start, but that doesn't mean it will produce the desired response for every patient.
Take acne as an example. Azelaic acid is one of the topical therapies included in the current AAD acne guidelines. If a patient's acne remains inadequately controlled, the dermatologist may reassess the treatment plan and consider another topical therapy, an oral medication such as doxycycline, or a combination approach based on the type and severity of acne and other patient-specific factors.
That doesn't mean the topical medication was a "weaker" treatment. It means the initial approach did not achieve the desired response for that particular patient, so it may be time to adjust the treatment strategy.
Sometimes the Treatment Plan Isn't Practical
A treatment can only provide its intended benefit if the patient can realistically follow the prescribed regimen.
Onychomycosis, commonly known as toenail fungus, is a good example. Some prescription topical antifungals require a surprisingly long commitment. Efinaconazole 10% solution, for example, is generally applied once daily for 48 weeks.
That's almost a year of remembering to treat the nail every single day.
The American Academy of Dermatology specifically advises patients who find it difficult to use efinaconazole for the prescribed length of time to discuss it with their dermatologist. The AAD also explains that treatment options for nail fungus include both topical and oral antifungal medications. Which approach is selected can depend on factors such as the extent of nail involvement, the type of fungus, the patient's health, other medications, and individual treatment considerations.
For some patients, maintaining a long topical regimen may be realistic. For others, a dermatologist may determine that an oral antifungal or another treatment approach is more appropriate after considering the potential benefits, risks, contraindications, drug interactions, and the patient's individual circumstances.
The point isn't that the oral medication is automatically "stronger."
It's that a treatment isn't truly practical if the patient cannot realistically follow the regimen long enough to achieve the intended result.
Sometimes It's Time to Change the Strategy
Treatment plans aren't set in stone. Dermatologists may adjust therapy based on how the condition and the patient respond after treatment begins.
A change may be considered when:
The condition has not responded adequately to the initial treatment.
The disease has progressed or become more extensive.
The treatment regimen is difficult for the patient to maintain.
The risks and benefits begin to favor a different treatment.
The patient's circumstances or treatment goals change.
Changing the strategy also doesn't always mean abandoning topical therapy. In acne treatment, for example, the AAD recommends combining systemic antibiotics with benzoyl peroxide and other topical therapies rather than necessarily treating oral and topical medications as an either-or decision. The guidelines also recommend limiting systemic antibiotic use when possible.
That is not evidence that oral medication was "better" all along. It is evidence that dermatologic treatment should evolve based on the condition, the patient's response, and what is realistically achievable.
Local Treatment vs. Systemic Treatment: It's About the Target
Here's perhaps the easiest way to remember all of this.
If the therapeutic target is primarily localized to the skin, direct topical therapy may make pharmacologic sense.
If disease is severe, widespread, difficult to reach topically, associated with systemic involvement, or inadequately controlled with topical therapy, systemic treatment may make more sense.
And sometimes the answer is both.
The AAD's psoriasis guidance, for example, explicitly recognizes that topical medications can be combined with systemic agents.
Dermatologists aren't choosing between Team Cream and Team Pill.
They're choosing among therapeutic tools based on the patient in front of them.
Why the “Strongest” Treatment Isn't Always the Best Treatment
Patients understandably want something that works.
But in medicine, effectiveness isn't simply a contest to find the most aggressive medication.
Treatment decisions involve balancing potential benefit against adverse effects, disease severity, treatment burden, patient preferences, medical history and other individual considerations.
The best medication is therefore not necessarily the one that reaches the most parts of your body.
It's the one that appropriately treats your condition, at your level of severity, with an acceptable balance of benefits and risks.
Sometimes that's a tablet.
Sometimes it's a cream.
Sometimes it's a combination.
And yes—sometimes dermatology really does come down to choosing between several tubes that look almost identical in your bathroom cabinet.
The real question isn't:
“Which one is stronger?”
It's:
“Which treatment makes the most sense for this condition and this patient?”
And that's exactly the question a board-certified Telederm dermatologist is trained to answer.
Have a board-certified dermatologist walk through your treatment options.
$45 per medical visit — a board-certified dermatologist reviews your skin and builds a custom plan.
This article is for educational purposes only and is not a substitute for professional medical advice — talk to your dermatologist about what's right for you. Compounded medications are prepared by a licensed pharmacy to meet individual patient needs and are not FDA-evaluated in the same way as commercially manufactured drugs.
Knox Beasley, MD, FAAD
Dermatologist · Tulane University School of Medicine
Acne, Rosacea, Scalp conditions
Keep reading.
All in Dermatology Myths, Explained →
Myth #3: Pores Can Open and Close
Pores can look more noticeable for plenty of reasons. This post breaks down the myth and explains what actually changes the way they look.
 Telederm Clinical Team · Sep 21, 2026

Myth #2: Dark Circles Mean You Need More Sleep
A good night’s sleep doesn’t always make dark circles disappear. From genetics and pigmentation to allergies and natural shadows, there may be more happening beneath your eyes than simply being tired.
Telederm Clinical Team · Sep 9, 2026
Myth #1: Oily Skin Doesn't Need Moisture
If your skin already feels oily, adding moisturizer might sound like the last thing you need. But oil and moisture tell two different stories.
Telederm Clinical Team · Aug 24, 2026
Vitiligo Treatment Has Changed: Understanding Today’s Options
Vitiligo treatment has evolved as researchers learn more about the immune pathways behind pigment loss. From established topical therapies and phototherapy to newer JAK-targeted approaches, understanding the options can help patients have more informed conversations about treatment.
Telederm Clinical Team · Sep 28, 2026